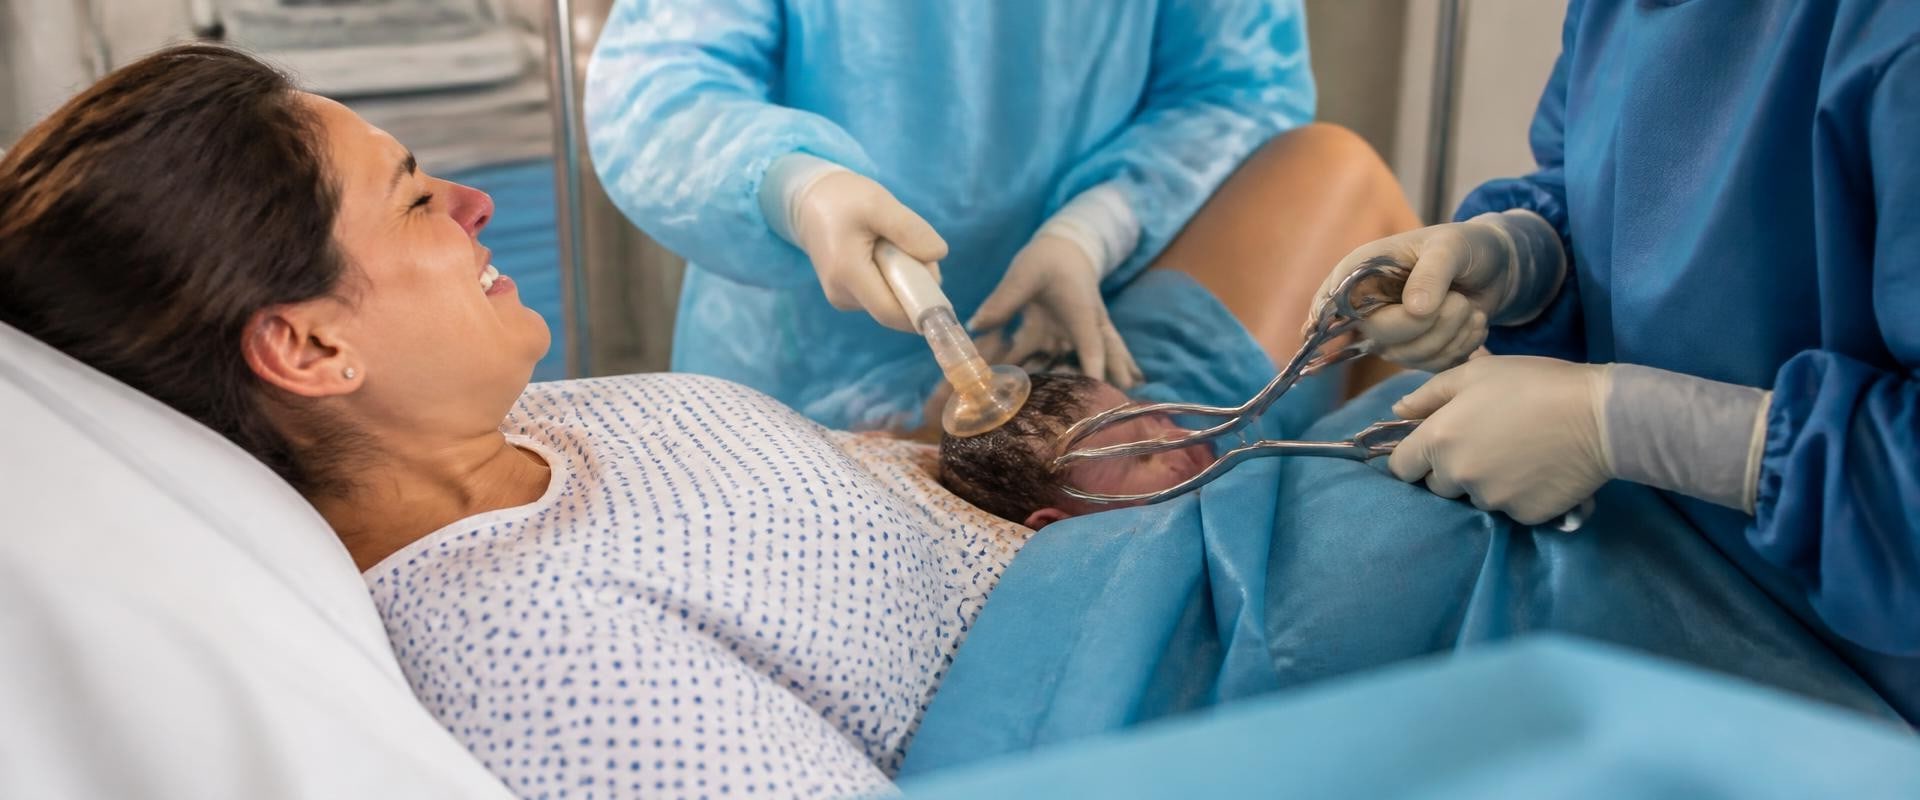
Forceps and vacuum extraction are two methods used to assist certain vaginal deliveries. Both can help complete childbirth when continued pushing is unsuccessful or rapid delivery is needed. Their injury patterns differ, and using both instruments during the same delivery can increase risks. The safest choice depends on the clinical circumstances and the experience of the medical team.
How forceps and vacuum extraction differ
Forceps are curved instruments placed around the baby's head.
They allow the clinician to apply controlled traction and, in selected cases, assist with rotation.
Vacuum extraction uses a suction cup attached to the baby's scalp.
The clinician applies traction during contractions while the mother pushes.
Both procedures fall under operative vaginal delivery.
Neither method is appropriate for every patient.
The choice depends on fetal position, how far the head has descended, maternal health, and other factors.
Why an assisted delivery may be recommended
A prolonged second stage of labor is one possible reason.
Another is concern about the baby's condition based on fetal monitoring.
Certain maternal health conditions may also make prolonged pushing undesirable.
When performed appropriately, an assisted vaginal delivery may avoid some risks associated with emergency surgery.
However, the clinician must consider whether the attempt is likely to succeed safely.
Comparing newborn injury risks
Forceps may cause facial bruising, facial nerve compression, and other head injuries.
Vacuum extraction is more strongly associated with certain scalp injuries.
These include cephalohematoma and, rarely, subgaleal hemorrhage.
Both procedures can be associated with intracranial bleeding.
The exact risks depend on the delivery circumstances.
A baby who has already experienced prolonged or difficult labor may have additional risk factors independent of the instrument selected.
Maternal injury risks
Forceps-assisted delivery is associated with a greater risk of severe perineal tears than vacuum-assisted delivery.
Third- and fourth-degree tears involve the anal sphincter and, in the most severe cases, the rectal lining.
These injuries may require surgical repair and follow-up.
Vacuum extraction generally causes less severe maternal soft-tissue trauma, although it has its own risks.
The clinician must balance potential benefits and complications for both mother and baby.
Why sequential instrument use matters
Sequential instrument use means attempting delivery with one device and then switching to another.
For example, a vacuum attempt may be followed by forceps.
This approach has been associated with increased neonatal injury risks, including intracranial hemorrhage.
Clinical guidance generally discourages routine sequential use.
If an assisted delivery attempt is unsuccessful, the medical team must reassess the situation.
Cesarean delivery may be necessary.
Choosing the safest delivery approach
A successful assisted vaginal delivery depends on appropriate patient selection.
The cervix must be fully dilated.
The fetal head should be engaged, and its position must be known.
Adequate pain management and informed consent are also important.
An experienced operator must be prepared to stop when the attempt is not progressing safely.
Did you know?
A procedure that carries a higher risk of one type of injury may carry a lower risk of another.
This is why comparing forceps and vacuum delivery requires considering both newborn and maternal outcomes.
Common questions around forceps and vacuum delivery
Is vacuum extraction always safer than forceps?
No. Each method has different risks and benefits.
Can doctors switch from vacuum to forceps?
Sequential use is generally discouraged because of increased injury risks, although unusual circumstances require individual clinical judgment.
Does forceps delivery cause more maternal tearing?
Forceps are associated with higher rates of severe perineal trauma than vacuum extraction.
